Kawasaki Disease
Kawasaki disease is an acute febrile multisystem vasculitis of childhood that predominantly affects medium-sized arteries.
It is characterized by three important features:
- Mucocutaneous changes
- Cervical lymphadenitis
- Medium-sized artery vasculitis
Although different medium-sized arteries can be involved, the coronary arteries are particularly important because coronary involvement determines the major complications of the disease.
Why is Kawasaki Disease Important?
Kawasaki disease is an important cause of acquired heart disease in children.
The disease is usually self-limited, but involvement of the coronary arteries can result in coronary artery aneurysms, thrombosis, myocardial ischemia, myocardial infarction, and even sudden death.
Early recognition and treatment are therefore extremely important.
Epidemiology
Kawasaki disease primarily affects infants and young children.
- About 80% of cases occur below 5 years of age.
- Peak incidence is around 2 years of age.
- Boys are affected more commonly than girls.
- Although originally described in Japan, the disease occurs worldwide.
Pathogenesis
The exact cause of Kawasaki disease is unknown.
It is thought to represent an immune-mediated vascular injury occurring in genetically susceptible children, possibly triggered by infections, particularly viral infections.
The immune response ultimately results in inflammation of medium-sized arteries, with the coronary arteries being particularly important.
Clinical Features
The clinical course can be divided into three phases:
- Acute phase
- Subacute/convalescent phase
- Recovery phase
Acute Phase
The acute phase usually occurs during the first 1–2 weeks.
Important manifestations include:
- High-grade fever
- Bilateral conjunctival congestion
- Red lips and oral cavity
- Strawberry tongue
- Edema of palms and soles
- Cervical lymphadenopathy
- Skin rash
These mucocutaneous manifestations explain why Kawasaki disease was originally described as a mucocutaneous lymph node syndrome.
Subacute Phase
The subacute phase is characterized by desquamation of the fingertips.
This is an important period because coronary artery aneurysms and thrombosis may develop during this phase, even though the fever has subsided.
Recovery Phase
Clinical manifestations gradually resolve and inflammation subsides.
Coronary artery abnormalities may regress in some patients, while in others they may persist and result in complications.
Coronary Artery Involvement
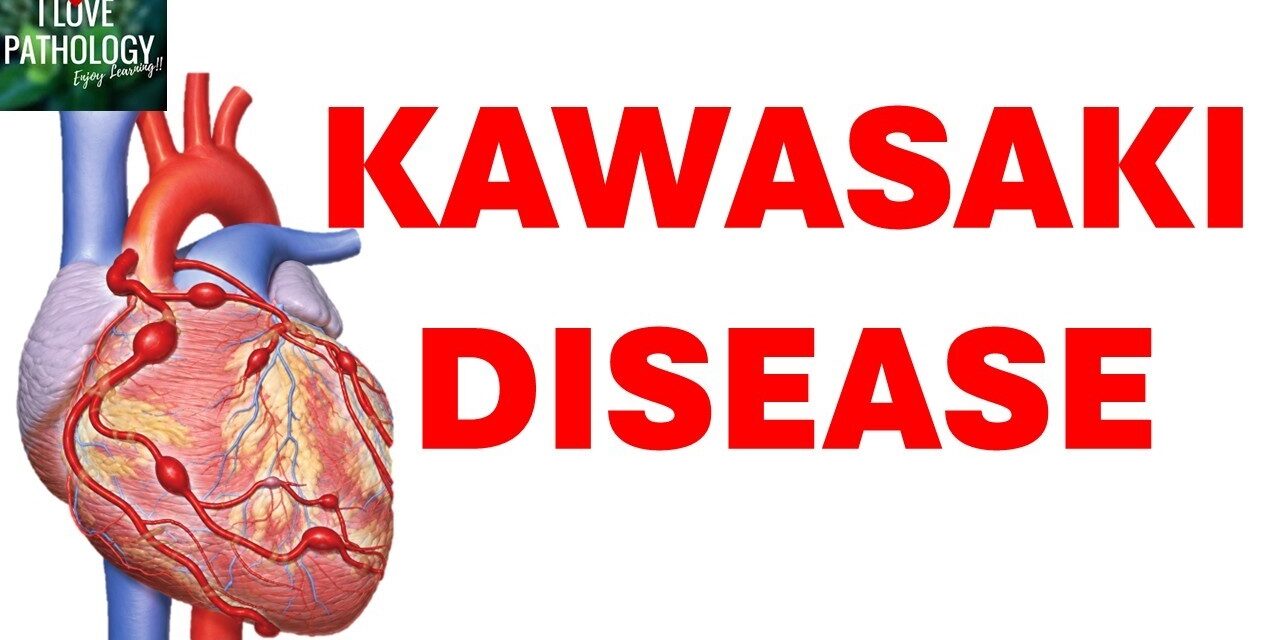
Coronary artery involvement is the most important complication of Kawasaki disease.
Coronary arteritis can weaken the arterial wall, resulting in formation of coronary artery aneurysms.
In untreated patients, coronary artery aneurysms may occur in about 25% of cases.
These aneurysms may be complicated by:
- Thrombosis
- Myocardial ischemia
- Myocardial infarction
- Rupture
- Sudden death
Thus, the prognosis of Kawasaki disease is closely related to the extent of coronary artery involvement.
Pathology
Grossly, the affected arteries may show:
- Dilatation
- Bead-like aneurysms
- Thrombus formation
- Irregularity of the arterial wall
Microscopically, there is inflammation of the vessel wall, predominantly consisting of mononuclear inflammatory cells, including lymphocytes, plasma cells, and monocytes.
Compared with polyarteritis nodosa, fibrinoid necrosis is less prominent.
Healing may result in intimal thickening.
Laboratory Findings
Laboratory findings are generally nonspecific and may include:
- Increased ESR
- Increased C-reactive protein
- Leukocytosis
- Thrombocytosis, particularly during the subacute phase
There is no single specific diagnostic test for Kawasaki disease. Diagnosis therefore depends on clinical findings and clinicopathological correlation.
Radiological evaluation is particularly useful for detecting coronary artery abnormalities.
Treatment
Early treatment is crucial.
The main treatment discussed in the video includes:
- Intravenous immunoglobulin (IVIG)
- Aspirin
Early treatment markedly reduces the risk of coronary artery complications.
Kawasaki Disease vs Polyarteritis Nodosa
| Feature | Kawasaki Disease | Polyarteritis Nodosa |
|---|---|---|
| Typical age | Children | More common in adults |
| Vessel involved | Medium-sized arteries | Medium-sized arteries |
| Coronary involvement | Prominent | Minimal |
| Fibrinoid necrosis | Less prominent | More prominent |
Summary
- Kawasaki disease is an acute febrile medium-vessel vasculitis of childhood.
- Think of Kawasaki disease in a child with prolonged fever and mucocutaneous manifestations.
- Strawberry tongue, conjunctival congestion, edema of palms and soles, rash, cervical lymphadenopathy, and fingertip desquamation are important clues.
- Coronary artery involvement determines the major complications and prognosis.
- Coronary artery aneurysms may lead to thrombosis and myocardial infarction.
- Early recognition and treatment with IVIG are crucial.
- Kawasaki-like illness or multisystem inflammatory syndrome in children (MIS-C) is an important consideration in the setting of SARS-CoV-2 infection.
Want to Understand Kawasaki Disease Better?
Why are the coronary arteries so important in Kawasaki disease? When do coronary aneurysms develop? How does the disease progress through its different phases, and how can you distinguish it from polyarteritis nodosa?
▶️ Watch the complete ILovePathology video for the clinical images, phase-wise progression, coronary artery pathology, comparison with PAN, treatment details, and discussion of MIS-C.